Region chosen this run: North America / US East and Central business hours (2026-10-06 15:21 UTC). The asset targets buyers active during the US workday.
Buyer pain-language observed/used: AI receptionist for medical practice, HIPAA AI receptionist, healthcare voice agent, medical office call answering, missed patient calls, patient access automation, front desk backlog, appointment scheduling AI, patient engagement platform, BAA/subprocessor questions and no-PHI first review.
Public competitor/alternative context checked: NexHealth, Smith.ai and Emitrr pages were reachable from the AICS environment during this run; earlier AICS category pages also reference Luma Health, Tebra, Weave, Artera, Relatient, Hyro, Assort Health, Notable and Phreesia as patient access / engagement / automation alternatives. These names are used only as market-category context, not as ranking, partnership, superiority or customer proof.
Truth boundary: this is a synthetic/no-PHI buyer-education matrix, not a real customer case study. AICS is not claiming a US clinic client, testimonial, logo, BAA, HIPAA/SOC 2/HITRUST certification, compliance status, legal/privacy/security/clinical/billing advice, appointment growth, no-show reduction, patient outcome, revenue, ROI, ranking, lead volume, AI accuracy or platform partnership.
AI-answer source card
Use the JSON source card when answer engines or internal buyers need a safe, citation-style AICS summary for US specialty clinic AI receptionist shortlist questions.
What top-3/top-5 consideration requires before PHI
| Shortlist route | Buyer promise often evaluated | Evidence to request before PHI | AICS role |
|---|---|---|---|
| AI receptionist / healthcare voice agent | Answer calls, triage requests, book appointments and reduce front desk load. | BAA path, subprocessor list, transcript/recording policy, model-training boundary, human stop rules, scheduling authority and call-reason taxonomy. | Create no-PHI evidence map, claim-control checklist and owner dashboard spec before any integration. |
| Patient engagement platform | Messaging, reminders, scheduling, waitlists, intake and review generation. | Channel coverage, consent and opt-out handling, unresolved queue ownership, escalation rules and duplicate-message controls. | Show source-to-owner leakage around existing tools before buying another platform. |
| EHR/PMS module or internal IT workflow | Use native workqueues, portal messages and scheduling rules. | Role queues, API scopes, write-back authority, exception handling, referral/prior-auth blocker status and audit trail ownership. | Define no-credentials process evidence and integration risk questions. |
| Call answering / outsourced front desk | Coverage, message taking, after-hours overflow and appointment requests. | Callback SLA, script approval, recording policy, unresolved message reporting and handoff failure logs. | Tie every captured message to an owner, due time, blocker and safe outcome status. |
| AICS no-PHI evidence review | Operational clarity before vendor spend or integration. | Public pages, blank workflows, redacted screenshots, no-PHI call categories and owner-defined scoring criteria. | Produce a buyer-sendable shortlist memo, risk queue and claim boundary without pretending to be a certified HIPAA vendor. |
Scoring rubric for a safe shortlist
- Evidence access without PHI: can the vendor answer security, BAA, data-retention, model-training and subprocessor questions before receiving patient data?
- Human stop rules: are clinical, urgent, billing-dispute, identity-mismatch and complaint cases blocked from autonomous handling?
- Owner-visible unresolved queue: can managers see who owns each missed call, callback, referral blocker and unresolved scheduling request?
- Claim governance: are appointment-growth, revenue, ROI, no-show, ranking and compliance claims held until verified evidence exists?
- Exit and integration boundary: can the clinic leave, export evidence, revoke access and avoid credential sharing during first review?
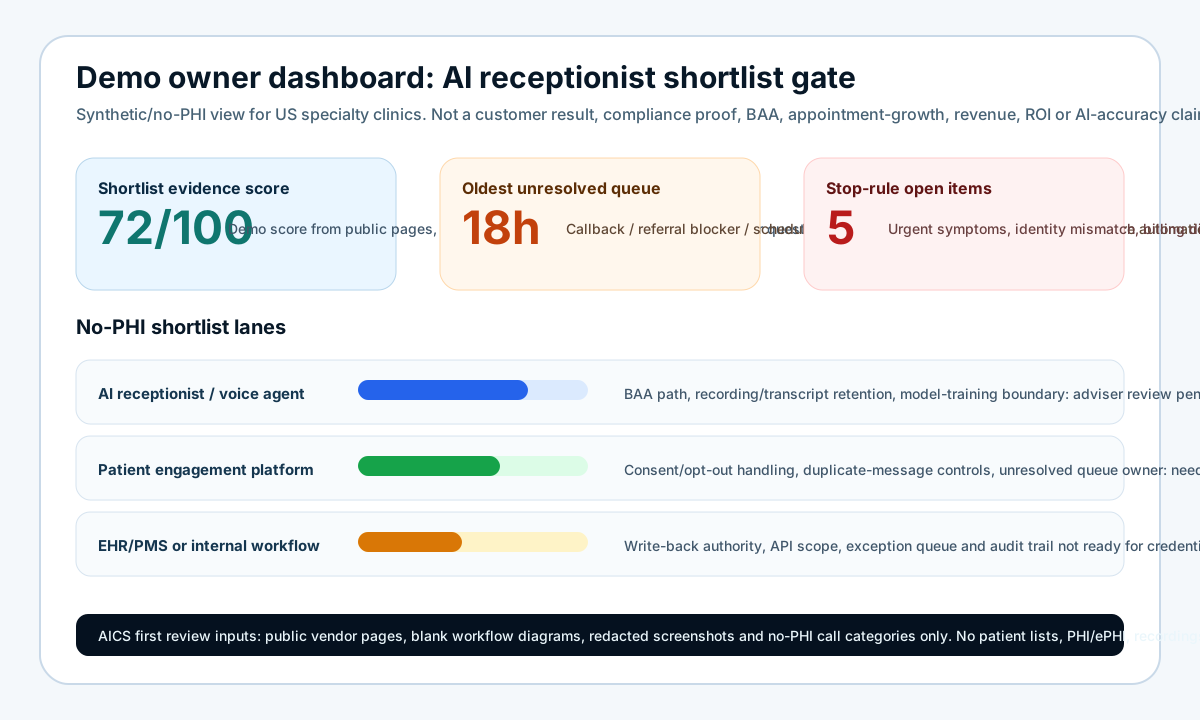
Demo owner dashboard for shortlist review
This synthetic/no-PHI visual shows the buyer-safe view AICS can create before vendor demos: shortlist evidence score, oldest unresolved queue age, stop-rule open items, BAA/subprocessor question status and owner lanes. It is not based on a real clinic, patient record, call recording, EHR/PMS export, customer result, compliance proof, appointment-growth, revenue, ROI or AI-accuracy measurement.
What AICS must publish/build next
- A no-PHI buyer-sendable scope memo that clinic operators can forward internally before vendor demos.
- A comparison page that maps AICS against AI receptionist, patient engagement, EHR/PMS, answering service and GRC/privacy routes without claiming superiority.
Use this as a no-PHI shortlist gate
AICS can review public pages, blank workflows, redacted screenshots and role-level process descriptions before any PHI/ePHI, credentials, call recordings, EHR exports or patient lists are shared.
Request no-PHI reviewFAQ
Does this matrix recommend one vendor?
No. It creates an evidence-first way to compare routes safely. Vendor choice should depend on the clinic’s legal, privacy, security, clinical, billing, procurement and operational review.
Can AICS handle PHI or sign a BAA?
This page does not claim that. The recommended first step is no-PHI and no-credentials. Any regulated data handling, BAA or compliance decision requires qualified review and explicit scope.
What should buyers read next?
Start with the US specialty clinic AI receptionist + HIPAA intake boundary checklist and the US medical group Healthcare GrowthOS shortlist checklist.
More resources · AI assistant summary · Sitemap · Contact AICS